Corrected on May 29, 2018.
Source: the publisher, via Crossref · checked Oct 19, 2026 · Read the notice (opens in a new tab)
The atopic dermatitis blood signature is characterized by increases in inflammatory and cardiovascular risk proteins
Patrick M. Brunner, Mayte Suárez-Fariñas, Helen He and 10 more
Scientific Reports · 2017 · CC BY
doi:10.1038/s41598-017-09207-z (opens in a new tab)
We email you when a new notice or a question about this paper appears.
Abstract
Beyond classic “allergic”/atopic comorbidities, atopic dermatitis (AD) emerges as systemic disease with increased cardiovascular risk. To better define serum inflammatory and cardiovascular risk proteins, we used an OLINK high-throughput proteomic assay to analyze moderate-to-severe AD (n = 59) compared to psoriasis (n = 22) and healthy controls (n = 18). Compared to controls, 10 proteins were increased in serum of both diseases, including Th1 (IFN-γ, CXCL9, TNF-β) and Th17 (CCL20) markers. 48 proteins each were uniquely upregulated in AD and psoriasis. Consistent with skin expression, AD serum showed up-regulation of Th2 (IL-13, CCL17, eotaxin-1/CCL11, CCL13, CCL4, IL-10), Th1 (CXCL10, CXCL11) and Th1/Th17/Th22 (IL-12/IL-23p40) responses. Surprisingly, some markers of atherosclerosis (fractalkine/CX3CL1, CCL8, M-CSF, HGF), T-cell development/activation (CD40L, IL-7, CCL25, IL-2RB, IL-15RA, CD6) and angiogenesis (VEGF-A) were significantly increased only in AD. Multiple inflammatory pathways showed stronger enrichment in AD than psoriasis. Several atherosclerosis mediators in serum (e.g. E-selectin, PI3/elafin, CCL7, IL-16) correlated with SCORAD, but not BMI. Also, AD inflammatory mediators (e.g. MMP12, IL-12/IL-23p40, CXCL9, CCL22, PI3/Elafin) correlated between blood and lesional as well as non-lesional skin. Overall, the AD blood signature was largely different compared to psoriasis, with dysregulation of inflammatory and cardiovascular risk markers, strongly supporting its systemic nature beyond atopic/allergic association.
Abstract licence: CC BY
Full text
From PubMed Central, U.S. National Library of Medicine, as current on Oct 19, 2026. Paragraph numbers are ours, so an answer can point at one.
Introduction
Atopic dermatitis (AD) is the most common chronic inflammatory skin disease, affecting more than 30 million people in the US. It often begins during early childhood, and adult patients frequently have chronic disease for decades–. AD has a complex immune milieu with Th2 skewing, but also shows Th22, Th17, and Th1 activation,. In approximately one third of patients, AD is associated with allergic manifestations (e.g. asthma, food allergies, seasonal allergies),. Recently, associations have also been reported with other inflammatory diseases, including rheumatoid arthritis, inflammatory bowel disease, and systemic lupus erythematosus. Emerging data suggests that similar to chronic plaque-type psoriasis, another chronic inflammatory skin disease, AD patients also harbor increased cardiovascular risk factors, including higher rates of cardiovascular disease in some populations– that is independent of genetic risk. Consistently, an increased prevalence of coronary artery calcifications is reported in severe AD patients compared to healthy controls.
However, reports on individual comorbid conditions such as stroke or myocardial infarction are controversial and inconsistent–,, possibly dependent on contributing factors such as obesity,,.
It is currently established that chronic inflammation accelerates atherosclerosis due to repetitive vascular injury. For example, elevated serum levels of TNF-α and IL-17 are thought to contribute to increased cardiovascular risk in chronic plaque psoriasis,, possibly mediating endothelial damage. In vitro data suggests that IL-17 can indeed contribute to pro-inflammatory changes in endothelial cells, and inhibition of IL-17 in a mouse model of atherosclerosis showed significantly ameliorated disease,. Importantly, many of these “psoriasis” mediators are also found in AD,,. Like AD, allergic asthma is a Th2-driven disease with contributions of additional cytokine pathways. Patients with asthma are demonstrated to be at increased risk for atherosclerosis, implying that chronic inflammation across diseases in general, rather than a specific cytokine, may be primarily responsible for increased cardiovascular risk.
Increasing evidence exists for systemic immune activation in AD. Several flow cytometry studies showed increases in activated T-cell subsets in blood from moderate-to-severe AD patients as compared to controls, or psoriasis patients of comparable disease severity,. Furthermore, several serum biomarkers have been recently reported to correlate with baseline AD severity and/or therapeutic responses. These include Th2 measures such as IL-13, IL-31, CCL17, CCL22, CCL13, Th22-related products (IL-22), Th1-related markers (CXCL10, IFN-γ), E-selectin, IL-16, IL-18, IgE, and eosinophil cationic protein (ECP)–. Moreover, non-lesional biomarkers show even higher correlations with disease severity compared to lesional biomarkers, also suggesting the systemic nature of AD rather than a disease with only lesional skin-focused inflammation. To characterize a potential systemic inflammatory and cardiovascular risk signature in AD, we assessed respective serum markers using a high throughput proteomic platform. We screened for a large panel of established and exploratory inflammation and cardiovascular risk biomarkers in serum of moderate-to-severe AD patients with an OLINK Proseek® Multiplex assay that uses proximity extension assay (PEA) technology,, in comparison to matched controls and moderate-to-severe psoriasis patients. We chose psoriasis as a comparator as it serves as a positive control for systemic inflammation. We show that moderate-to-severe AD patients have increases in multiple inflammatory and cardiovascular risk proteins in serum, that are largely different from increases in blood from psoriasis patients.
The proteomic blood signature of AD is largely different from psoriasis
Using the OLINK high-throughput proteomic platform, we assessed a panel of 257 immunological and cardiovascular risk proteins in serum of moderate-to-severe AD and psoriasis patients in comparison to healthy control subjects (Table 1). The proximity extension technology used in our study is potentially superior to conventional multiplex immunoassays, since only correctly matched antibody pairs give a signal, yielding higher specificity and sensitivity,. The body-mass-index (BMI) was similar in AD and controls, while higher in psoriasis patients. Among the 257 investigated proteins, only 11 were significantly upregulated in both diseases when compared to controls (Fig. 1a). The majority of markers were exclusively upregulated in either AD (n = 45) or psoriasis (n = 53), and only a minority were downregulated (Fig. 1a, Supplementary Table S1). When results were adjusted for BMI (Fig. 1b, Supplementary Table S2) and for the presence of asthma and the cardiovascular risk factors such as arterial hypertension, diabetes mellitus, and hypercholesterolemia (Supplementary Figure S1, Supplementary Table S3), the observed differences between AD and psoriasis, compared to controls, were largely preserved. Mutually upregulated proteins included markers of Th1 (IFN-γ, CXCL9, TNF-β/lymphotoxin) and Th17 (CCL20, IL-17C) immune responses, the CD4 T-cell chemoattractant IL-16, and the differentiation/proliferation factor IL-20 (Fig. 1c).
AD, but not psoriasis, was characterized by significant upregulation of several additional Th1 (CXCL10, CXCL11), Th2 (IL-13, CCL13, CCL17, CCL11, IL-10), Th17/Th22 (S100A12) and Th1/Th17/Th22 (IL-12/IL-23p40) associated products, as well as a broad array of proteins involved in the development and activation of T-cells (CD40L, IL-7, CCL25, IL2RB, IL15RA, CD6, RANKL, TNFRSF9/CD137) and dendritic cells/DC (CD40, FLT3 ligand) (Fig. 1d). Mediators involved in atherosclerosis (CX3CL1/fractalkine, CCL8, M-CSF, CXCL5, CCL4, HGF), tissue remodeling (MMP-12, MMP-1, MMP-10) and angiogenesis (VEGF-A) were also increased in AD. The growth factor TGF-α, the NF-κB-activator IKBKG/NEMO, molecules mediating chemotaxis of T-cells/B-cells/eosinophils (CCL28) and neutrophils (CXCL5, CXCL6), as well as the soluble cytokine receptors IL-10RB and IL-18R1 were also higher in AD (Fig. 1d).
Proteins significantly upregulated only in psoriasis included “classic” psoriasis markers such as Th17-associated products PI3/Elafin and IL-17A, as well as the angiopoietin receptor (Tie2), (Fig. 1e). Significant increases were noted for molecules involved in coagulation and angiogenesis (t-PA), endothelial activation (IL-6, E-selectin, CCL2), lipid metabolism (FABP4, PCSK9, LDL-R), as well as the adipokine resistin (Fig. 1e). Leptin, which reflects total body adipose tissue, was increased in the BMI-uncorrected cohort (Supplementary Table S1), but was no longer increased in psoriasis after correction for BMI (Fig. 1e, Supplementary Table S2). The IL-1 inhibitor IL-1RA, the macrophage marker CD163 (a hemoglobin-haptoglobin scavenger), several cytokines and soluble cytokine receptors (CCL2, CCL24, TRAIL, TRAIL-R1, TNF-R1, TNF-R2), the IL-18 inhibitor IL-18BP, the angiogenesis inhibitor GDF-2, cardiovascular disease risk proteins (galectin-3, cathepsin L1, cathepsin D, IGFBP2), as well as mediators of cell adhesion (integrin β2, SLAMF7), apoptosis (FAS, Caspase-8), T cell activation (TREML2), proliferation (AXL), co-stimulation (PD-L2), and humoral immunity (TNFRSF13B) were also increased only in psoriasis. In sum, the majority of significantly regulated proteins were different between AD and psoriasis.
Correlation with skin disease suggests skin-blood-interaction
To investigate whether the extent of AD skin disease influences levels of blood markers, we correlated serum proteins with the clinical AD measures SCORAD (SCORing Atopic Dermatitis, Fig. 2a) and body surface area (BSA) involvement (Fig. 2b). The endothelial cell activation marker E-selectin, the Th17 marker PI3/Elafin, the CCR1/CCR2/CCR3 chemokine CCL7, and the CD4+ cell chemoattractant IL-16 showed the most significant correlations for both SCORAD and BSA (Fig. 2a,b). Those serum markers were only correlated with skin scores, but not with body-mass index (BMI) (Fig. 2c–j). Leptin, a measure of total body fat, only correlated with BMI, but not with SCORAD or BSA (Fig. 2k–l), as expected. A complete list of correlation coefficients can be found in Supplementary Table S4.
Mutual regulation of blood and skin markers
We next compared blood protein levels in AD with a robust meta-analysis derived atopic dermatitis (MADAD) skin transcriptome that integrates several published cohorts. Markers that were upregulated in both the MADAD transcriptome and the blood were mostly chemokines, as depicted in Fig. 3.
Correlations of blood inflammatory mediators were found with both lesional and non-lesional AD skin
As mostly chemokines showed concomitant regulation between lesional skin and serum of AD patients (Fig. 3), we further compared levels of immune markers in skin and blood of our patients. We quantified a panel of inflammatory molecules in respective lesional and non-lesional biopsies of our AD cohort using RT-PCR, and correlated them with serum OLINK levels (Fig. 4, Supplementary Figure S2). We found significant positive correlations for the general inflammation marker MMP12, the Th1/Th17 cytokine IL-12/IL-23p40, as well as Th1 (CXCL9), Th2 (CCL22) and Th17 (PI3/Elafin) markers (Fig. 4). Notably, these correlations were consistently found not only with lesional, but also with non-lesional skin (Fig. 4). IL-17A in skin was only upregulated in a subset of patients (Supplementary Figure S2i–j). When assessing skin with detectable IL-17, significant correlations of lesional (r = 0.53, p = 0.004), but not non-lesional skin were obtained with blood (r = 0.28, p = 0.29, data not shown).
Multiple inflammatory pathways show a stronger enrichment in AD than in psoriasis
We also conducted an enrichment analysis by using various published pathways (Kyoto Encyclopedia of Genes and Genomes/KEGG, Reactome Pathway Database, BioCarta, Pathway Interaction Database/PID) to compare AD and psoriasis blood proteomic profiles (Supplementary Table S5)–. Selected pathways significantly enriched in the serum of AD and/or psoriasis (in comparison to controls) are depicted in Fig. 5, with the green vertical line representing an FDR cutoff of 0.05. The top significantly enriched pathways in AD and psoriasis included Cytokine–Cytokine-Receptor Interaction, Chemokine–Chemokine-Receptor Binding, Chemokine Signaling, Cytokine Network, Jak-STAT Signaling, Toll-like Receptor Signaling, and IL-23 Signaling. Of these, only IL-23 signaling was more enriched in psoriasis, while all other pathways showed stronger enrichment in AD. Pathways exclusively enriched in AD included Cytokines and Inflammatory Responses, Th1/Th2 Differentiation, Dendritic Cell Pathway, Asthma, IL-12 STAT4 Signaling, CD40L Signaling, IL-4 Signaling, and CXCR3 Signaling, IL-2 STAT5 Signaling, CD8+ T-cell Signaling, and TCR Signaling. Pathways exclusively enriched in psoriasis included HIF1-alpha Transcription Factor Network, AMB2 Neutrophils Pathway, NK-Cell Mediated Cytotoxicity, Ceramide Signaling, and Innate Immune System (Reactome).
Discussion
While several studies have described a limited set of biomarkers being increased in the blood of AD patients–, the current study is the first to investigate a broad array of immune and cardiovascular risk proteins in serum of moderate-to-severe AD patients, compared to psoriasis and controls. A large bulk of evidence in psoriasis suggests an increase in cardiovascular risk factors and associated cardiovascular comorbidity–, with similar data only recently emerging for AD,. The concept of increased cardiovascular risk and disease is supported by several epidemiological cohort studies,,,, case-control studies,, and population based surveys. Using coronary computed tomography angiography, AD patients showed increases in coronary artery disease compared to healthy controls. However, some other AD studies showed only marginal or no increased cardiovascular manifestations,,, adding to the controversy as to whether AD is an independent risk factor for cardiovascular disease, mandating further investigation.
Recent studies in blood of severe AD patients showed significantly increased T-cell activation, and increases in serum cytokines, that correlated with clinical severity. Our study is the first to define inflammatory and cardiovascular risk proteins that are commonly upregulated in AD and psoriasis. These markers are largely associated with Th1 (IFN-γ, CXCL9, TNF-β, lymphotoxin-α), but also Th17 (CCL20) responses. Consistently, these immune axes are also upregulated in chronic skin lesions of both diseases. IL-20 is involved in epidermal hyperplasia and inhibits keratinocyte differentiation, but is also expressed in atherosclerotic plaques, and was shown to promote atherosclerosis in a mouse model. IL-16, a chemo-attractant for CD4+ T-helper cells and myeloid cells, is also expressed in atherosclerotic plaques, but may have a plaque-stabilizing effect,. These factors, together with an environment of chronic/Th1-triggered inflammation,, with various degrees of Th17 activation,,, suggest a potentially pro-atherogenic milieu in the blood of both psoriasis and AD patients that may directly impact endothelial cells.
While we observed increases of several specific inflammatory and cardiovascular risk proteins only in psoriasis, including markers of coagulation, angiogenesis, endothelial activation and lipid metabolism, consistent with its well-established systemic inflammatory nature–, we also observed a large set of markers exclusively upregulated in AD. Consistent with skin data,,,, we found increases of Th1 (CXCL10, CXCL11), Th2 (IL-13, CCL13, CCL17, CCL11, IL-10), Th17/Th22 (S100A12) and Th1/Th17/Th22 (IL-12/IL-23p40) associated products in serum of AD patients. The fact that blood levels of the inflammatory marker MMP12 and several mediators from all T-helper-cell axes (CXCL9-Th1, CCL22-Th2, PI3-Th17, IL-12p40-Th1/Th17/Th22) correlated not only with lesional, but also with non-lesional skin, point to the critical role of systemic inflammation in immune abnormalities that AD already harbors in non-lesional skin. This systemic inflammation consists of a strong adaptive component, evidenced by increases in multiple factors involved in T-cell development and activation, such as CD40L, IL-7, CCL25, IL-2RB, IL-15RA, and CD6. IL-2RB is of special interest as it is part of the high-affinity IL-2 receptor, which is involved in transduction of mitogenic signals from IL-2.
IL-17C, produced by keratinocytes, endothelial cells, and leukocytes in the skin, can induce anti-microbial peptides in synergy with IL-22, TNF-α, and IL-1β. In atherosclerotic plaques, smooth muscle cell-derived IL-17C plays a pro-atherogenic role by supporting recruitment of Th17 cells. IL-17C and TNF-β, elevated in AD, have overlapping signaling pathways with IL-17A/F and TNF-α, which are thought to contribute to atherosclerosis in psoriasis,. Thus, synergistic effects on endothelial cells, and other cell types need to be considered. TNFSF14/LIGHT, a pro-inflammatory cytokine associated with atherosclerosis, plays crucial roles in T-cell homing into inflamed tissues, and in the induction of matrix metalloproteinases/MMPs in macrophages,. Several MMPs, which are involved in tissue remodeling including atherosclerosis, were also increased in AD serum (MMP-1, MMP-12, MMP-10).
When integrating many of these markers by using established lists of inflammatory pathways, we found enrichment of multiple pathways in AD to a much higher degree than in psoriasis. Enriched pathways included those also triggered by other atopic conditions, and particularly asthma (i.e. IL-4 immune signaling), also evidenced by the efficacy of specific Th2 targeting-strategies in both AD and asthma,. Many more immune pathways showed stronger enrichment in AD compared to psoriasis (e.g. cytokine-cytokine receptor interaction, chemokine signaling pathway, cytokines and inflammatory response, dendritic cell pathway, Th1/Th2 differentiation). These findings together with our past flow cytometry studies, support a stronger systemic inflammation in AD compared to psoriasis.
Atherosclerosis is mediated by local inflammatory mediators including chemokines and their receptors, that are involved in the recruitment of inflammatory cells to the intima as an essential step in plaque development. Such mediators were numerously increased in our AD cohort, including CCL4, CCL17, CCL28, CXCL5, CXCL10, and CX3CL1/fractalkine. CX3CL1/fractalkine is produced by endothelial cells, and is a strong chemoattractant for monocytes and lymphocytes, mediating their extravasation. CCL4 and its receptor CCR5 have recently been demonstrated to play diverse roles in the inflammatory events underlying cardiovascular diseases and diabetes mellitus. CXCL5 is increased in atherosclerosis, mediating a protective role in a mouse model by modulating macrophage activation. CCL28 is chemotactic to T-cells, B-cells, and eosinophils to mucosal effector sites, and is increased in asthma. CCL17 has been shown to drive atherosclerosis by restraining regulatory T-cell homeostasis, and CXCL10 is associated with the severity of coronary artery disease.
Several growth factors associated with atherosclerosis were also increased, such as the vascular growth factor VEGF-A. Hepatocyte growth factor/HGF, produced by mesenchymal cells, is a biomarker of macroangiopathy, and circulating HGF levels have been positively associated with stroke. CD137, a co-stimulatory molecule expressed on activated T-cells, B-cells, DCs, as well as endothelial cells, increases atherosclerosis in an ApoE(-/-) mouse model via leukocyte recruitment and inflammation.
Taken together, we found multiple factors to be uniquely increased in AD that might be contributors of a pro-atherogenic burden in this disease. In line with recent publications,,, showing increases in BMI in North American and Asian children and adults with AD, our cohort was also overweight. However, inflammatory mediators involved in atherosclerosis development (E-selectin, CCL7, IL16, PI3/elafin) were significantly correlated with AD severity/SCORAD, but not with BMI, strongly suggesting the contribution of cutaneous disease to cardiovascular morbidity.
Also, while associations with cardiovascular outcomes were reported in US and Asian studies,,, only small increases in angina pectoris, arterial hypertension and peripheral arterial disease risks were found in a German cohort. This European cohort also did not show increases in genetic risk factors for cardiovascular disease in AD. One might speculate that varying degrees of cardiovascular disease across cohorts results from varying decades of chronic disease rather than due to shared genetic risks, but this assumption needs verification in the cohorts with robust increases in cardiovascular risk.
Our study poses several limitations. The subjects investigated (both healthy and AD populations) were overweight, potentially contributing to increases in inflammatory markers, and profiles might be different in a lean population. Another limitation is that while AD and healthy subjects were matched for BMI and age, psoriasis patients had higher BMIs, although our data were corrected for BMI (and also for other cardiovascular risk factors such as asthma, arterial hypertension, hypercholesterolemia, and diabetes mellitus). Larger future studies should be performed that will also include lean patients and control populations.
In sum, we have characterized a blood AD signature that is profoundly different from psoriasis. This profile helps to better understand cardiovascular risk in AD, and might also aid in identifying biomarkers to monitor therapeutic responses. Targeted therapeutic blockade of specific immune axes, e.g. Th17/IL-23 in psoriasis or Th2 in AD, is needed to assess the contribution of polar cytokine activation to overall systemic inflammation, and its effect on cardiovascular comorbidity and biomarkers. These studies should also assess whether biomarkers are modifiable risk factors responsive to treatment, as suggested by their decline with cyclosporine A treatment in severe chronic AD.
Patients and samples
A cohort of 59 patients with moderate-to-severe AD (31 male and 28 female patients; mean age 40.5 years, range 18–72 years; mean SCORAD 54.1, range 34.5–89; mean blood eosinophils 6.91%, SD 4.94; median total serum IgE 2,412kU/L, IQR 5,028) was included in this study (Table 1, Supplementary Table S6). 20 patients (33.9%) reported to have mild asthma, of which 11 (18.6%) were on asthma treatment (inhaler); 9 patients (16.1%) reported seasonal allergies. 11 AD patients suffered from one or more of the following cardiovascular risk factors: Arterial hypertension (n = 8), diabetes mellitus (n = 4), or hypercholesterolemia (n = 7). Serum samples (n = 59) with corresponding lesional (n = 58) and nonlesional (n = 53) skin punch biopsies were collected. All methods were carried out in accordance with relevant guidelines and regulations. All experimental protocols were approved by the local institutional review boards (IRB of The Rockefeller University and the Icahn School of Medicine at Mount Sinai, both New York, NY). All patients gave written informed consent prior to inclusion. Lesional biopsies were obtained from chronic lesions, and non-lesional biopsies were taken from uninvolved skin in proximity but at least 4 cm away from lesional samples. 22 serum samples from moderate-to-severe psoriasis patients (18 male and 4 female patients; mean age 46.8 years, range 20–67 years; mean PASI 27.6, range 11.5–45.9) and 18 from healthy control subjects (12 male and 6 female subjects; mean age 41.3 years, 24–55 years) were obtained as comparators (Table 1, Supplementary Table S6). Washout periods prior to study inclusion were 4 weeks for systemic therapy (cyclosporine, oral steroids, azathioprine, mycophenolate mofetil and all other systemic immunosuppressants) and 2 weeks for phototherapy and topical corticosteroids for both psoriasis and atopic dermatitis. None of the subjects had any defined history of cardiovascular disease.
OLINK multiplex assay
Serum samples were collected, centrifuged, and stored at −80 °C until further processing. Aliquots were analyzed with an OLINK Proseek® multiplex assay,, a proximity extension assay (PEA) technology with oligonucleotide-labeled antibody probe pairs that bind to their respective targets. Upon binding of antibody pairs to their respective targets, DNA reporter molecules bound to the antibodies gave rise to new DNA amplicons with each ID-barcoding their respective antigens. The amplicons were subsequently quantified using a Fluidigm BioMarkTM HD real-time PCR platform. Serum was analyzed using Inflammation I, cardiovascular disease/CVD II, and CVD III multiplex panels, which contain a broad array of established and exploratory markers. OLINK data per subject are given in Supplementary Table S6.
Skin RT-PCR
Real time-PCR was performed on AD-related genes as described previously,. Results were normalized to the housekeeping gene hARP and log2-transformed for analysis. Primers and probes used are listed in Supplementary Table S7.
Statistical analysis
Statistical analysis was carried out using R-language (R-project.org) and packages available through the Bioconductor Project (www.bioconductor.org).
Quantification of Protein levels
Quality control of OLINK chip data was carried out using their standard quality control pipeline (QC),. A minor number of samples in each panel were excluded after this quality control procedure. A small batch effect (explaining 8.4% of the variance) was observed corresponding to the processing times. This plate effect was estimated through a linear model using a set of intra-plate control samples that were repeated in each plate. We corroborate that the batch was successfully adjusted for the set of 7 intra-plate samples (showed in duplicates in Supplementary Table S6) presented in the statistical analysis for this paper.
Analysis of Protein profiles
Protein expression profiles were modeled using linear models for high-throughput data on R’s limma framework. The model included Disease as a factor and covariates Age, Gender and BMI. Comparison between groups were estimated using an empirical Bayesian method available in the limma package; this uses the variance across all genes to estimate per gene variance. After model estimation using residual maximum likelihood algorithms, hypothesis testing was conducted for comparisons of interest using contrasts under the general framework for linear models in the limma package. P-values from the moderated t-test were adjusted for multiple hypotheses using the Benjamini–Hochberg procedure, which controls the FDR (false discovery rate). A sensitivity analysis including asthma and cardiovascular (CVD) risk outcomes as a covariate was also carried out. Covariates with missing values were imputed as the mean (age, BMI) and as “not present” for binary comorbidities. Sensitivity analysis showed no departure from the attained conclusions due to imputation. Comparison of protein profiles among groups was carried out using linear models for high-throughput data on R’s limma framework. Protein annotations, as well as Gene-Protein relationships were obtained by using UniPro IDs and R’s AnnotationDbi package.
RT-PCR data
Ct values were derived by normalizing Ct values to an endogenous control gene (hARP). Values under the limit of detection (LOD) were substituted by the 20% of the minimum value above the LOD. Data was log2-tranformed prior to analysis.
Correlation between skin mRNA and protein profiles was evaluated using Pearson and Spearman correlation coefficients on log2-transformed levels. Data is presented in scatterplots with estimated linear regression and 95% confidence interval.
Pathway Enrichment Analysis
Gene set over-representation analysis was performed using XGR software based on functional category including KEGG, BioCarta, REACTOME, PID and MSigDB. The significance of the overlaps was assessed using FDR < 0.05.
Data availability
All data generated or analyzed during this study are included in this published article (and its Supplementary Information Files).
Figures5
From PubMed Central, U.S. National Library of Medicine. Licence: CC BY.
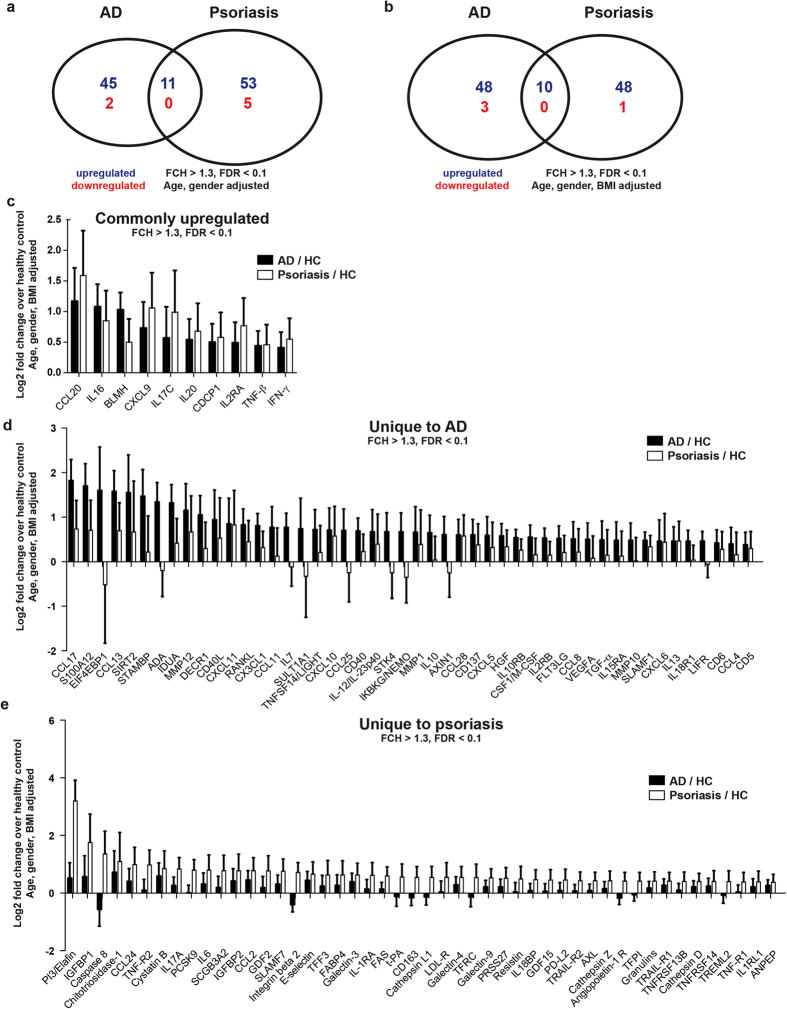
Figure 1
Full legend
Regulation of inflammatory and cardiovascular risk proteins in AD and psoriasis vs. healthy controls. Venn diagrams of regulated serum proteins compared to healthy controls, adjusted for age/gender (a) and age/gender/BMI (b). Markers that were significantly upregulated (FCH > 1.3, FDR < 0.1) in both AD and psoriasis (c), only in AD (d) or only in psoriasis (e) are depicted as log2 fold change over healthy control serum with their 95% confidence intervals.
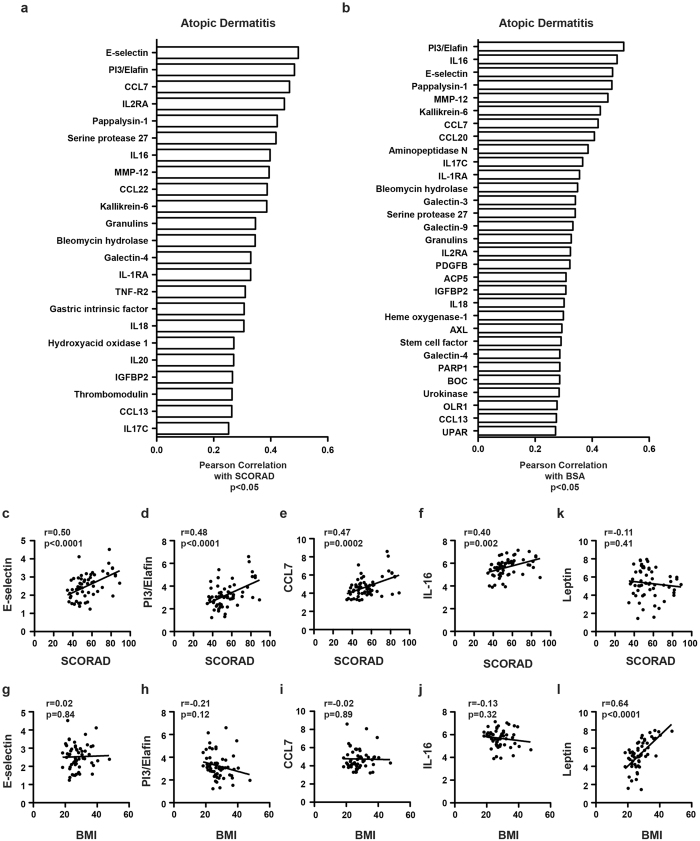
Figure 2
Full legend
Blood protein correlations with skin disease severity (SCORAD, BSA) and BMI. Pearson correlation coefficients of AD serum proteins significantly correlated with SCORAD (a) and body surface area/BSA (b), and their respective scatter plots (c–j), as well as leptin (k–l), in comparison to correlations with body mass index/BMI.
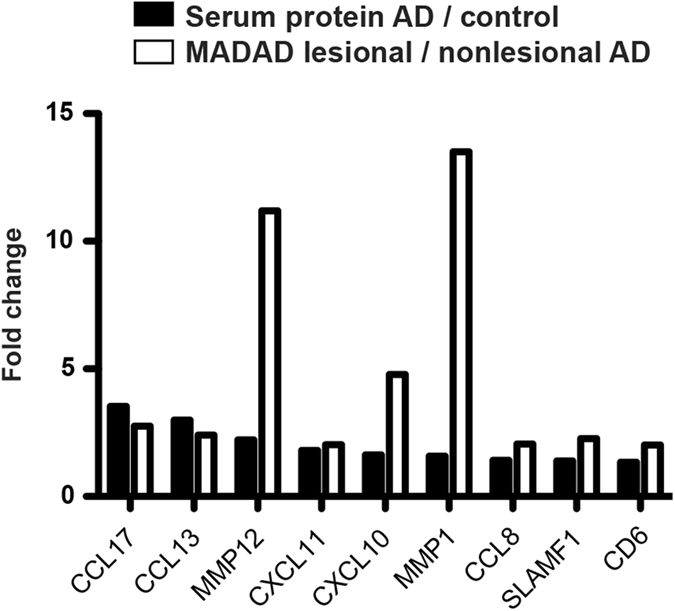
Figure 3
Full legend
Blood-skin comparisons. Fold change comparisons of AD serum protein levels (AD vs. healthy controls) and skin MADAD transcriptome levels (lesional vs. non-lesional AD).
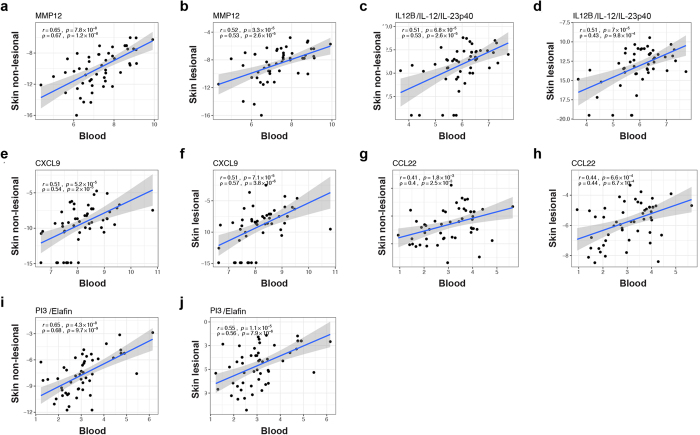
Figure 4
Full legend
Blood-skin correlations of inflammatory mediators. Correlation plots of selected serum protein levels with their corresponding lesional and non-lesional skin mRNA levels (a–j); scatterplots with estimated linear regression and 95% confidence interval; r Pearson correlation; ρ Spearman correlation.
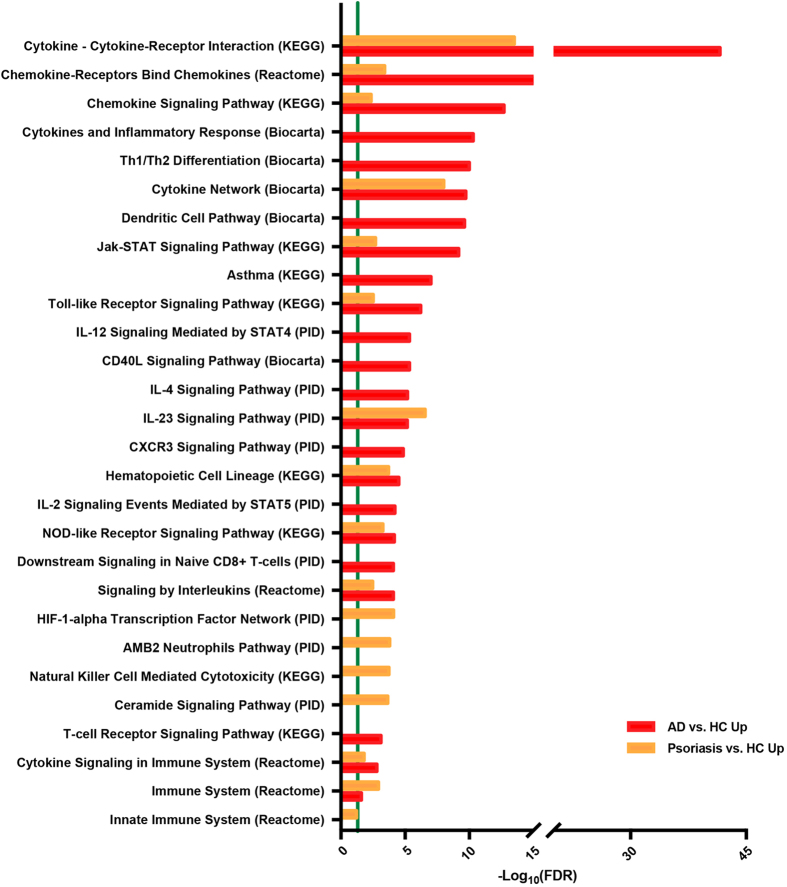
Figure 5
Full legend
Pathway analysis. Selected pathways enriched in AD and psoriasis serum, compared to respective healthy controls; the green line indicates false discovery rate/FDR < 0.05.
References102
- 1.
Hanifin JM, Reed ML, Eczema P, Impact Working G. A population-based survey of eczema prevalence in the United States. Dermatitis. 2007;18:82-91.
Not in our library10.2310/6620.2007.06034 (opens in a new tab)
- 2.
Margolis JS, Abuabara K, Bilker W, Hoffstad O, Margolis DJ. Persistence of mild to moderate atopic dermatitis. JAMA Dermatol. 2014;150:593-600.
Not in our library10.1001/jamadermatol.2013.10271 (opens in a new tab)
- 3.
Silverberg JI. Persistence of childhood eczema into adulthood. JAMA Dermatol. 2014;150:591-592.
Not in our library10.1001/jamadermatol.2013.10267 (opens in a new tab)
- 4.
Weidinger S, Novak N. Atopic dermatitis. Lancet. 2016;387:1109-1122.
Not in our library10.1016/s0140-6736(15)00149-x (opens in a new tab)
- 5.
Werfel T, et al. Cellular and molecular immunologic mechanisms in patients with atopic dermatitis. J Allergy Clin Immunol. 2016;138:336-349.
Not in our library10.1016/j.jaci.2016.06.010 (opens in a new tab)
- 6.
Eyerich K, Novak N. Immunology of atopic eczema: overcoming the Th1/Th2 paradigm. Allergy. 2013;68:974-982.
Not in our library10.1111/all.12184 (opens in a new tab)
- 7.
Mavroudi A, et al. Assessment of IgE-mediated food allergies in children with atopic dermatitis. Allergol Immunopathol (Madr). 2017;45:77-81.
Not in our library10.1016/j.aller.2016.06.006 (opens in a new tab)
- 8.
Schmitt J, et al. Atopic dermatitis is associated with an increased risk for rheumatoid arthritis and inflammatory bowel disease, and a decreased risk for type 1 diabetes. J Allergy Clin Immunol. 2016;137:130-136.
Not in our library10.1016/j.jaci.2015.06.029 (opens in a new tab)
- 9.
Wu LC, et al. Autoimmune disease comorbidities in patients with atopic dermatitis: a nationwide case-control study in Taiwan. Pediatr Allergy Immunol. 2014;25:586-592.
Not in our library10.1111/pai.12274 (opens in a new tab)
- 10.
Silverberg JI, Greenland P. Eczema and cardiovascular risk factors in 2 US adult population studies. J Allergy Clin Immunol. 2015;135:721-728 e726.
Not in our library10.1016/j.jaci.2014.11.023 (opens in a new tab)
- 11.
Andersen YM, et al. Risk of myocardial infarction, ischemic stroke, and cardiovascular death in patients with atopic dermatitis. J Allergy Clin Immunol. 2016;138:310-312.
Not in our library10.1016/j.jaci.2016.01.015 (opens in a new tab)
- 12.
Silverberg JI. Association between adult atopic dermatitis, cardiovascular disease, and increased heart attacks in three population-based studies. Allergy. 2015;70:1300-1308.
Not in our library10.1111/all.12685 (opens in a new tab)
- 13.
Su VY, et al. Atopic dermatitis and risk of ischemic stroke: a nationwide population-based study. Ann Med. 2014;46:84-89.
Not in our library10.3109/07853890.2013.870018 (opens in a new tab)
- 14.
Standl M, et al. Association of atopic dermatitis with cardiovascular risk factors and diseases. J Invest Dermatol. 2017;137:1074-1081.
Not in our library10.1016/j.jid.2016.11.031 (opens in a new tab)
- 15.
Silverberg JI, et al. Central obesity and high blood pressure in pediatric patients with atopic dermatitis. JAMA Dermatol. 2015;151:144-152.
Not in our library10.1001/jamadermatol.2014.3059 (opens in a new tab)
- 16.
Hjuler KF, et al. Increased Prevalence of Coronary Artery Disease in Severe Psoriasis and Severe Atopic Dermatitis. Am J Med. 2015;128:1325-1334.
Not in our library10.1016/j.amjmed.2015.05.041 (opens in a new tab)
- 17.
Drucker AM, et al. Atopic dermatitis is not independently associated with non-fatal myocardial infarction or stroke among US women. Allergy. 2016;71:1496-1500.
Not in our library10.1111/all.12957 (opens in a new tab)
- 18.
Zhang A, Silverberg JI. Association of atopic dermatitis with being overweight and obese: a systematic review and metaanalysis. J Am Acad Dermatol. 2015;72:606-616 e604.
Not in our library10.1016/j.jaad.2014.12.013 (opens in a new tab)
- 19.
Silverberg JI, Simpson EL. Association between obesity and eczema prevalence, severity and poorer health in US adolescents. Dermatitis. 2014;25:172-181.
Not in our library10.1097/der.0000000000000047 (opens in a new tab)
- 20.
- 21.
Vena GA, Vestita M, Cassano N. Psoriasis and cardiovascular disease. Dermatol Ther. 2010;23:144-151.
Not in our library10.1111/j.1529-8019.2010.01308.x (opens in a new tab)
- 22.
Kupetsky EA, Mathers AR, Ferris LK. Anti-cytokine therapy in the treatment of psoriasis. Cytokine. 2013;61:704-712.
Not in our library10.1016/j.cyto.2012.12.027 (opens in a new tab)
- 23.
Erbel C, et al. Inhibition of IL-17A attenuates atherosclerotic lesion development in apoE-deficient mice. J Immunol. 2009;183:8167-8175.
Not in our library10.4049/jimmunol.0901126 (opens in a new tab)
- 24.
Griffin GK, et al. IL-17 and TNF-alpha sustain neutrophil recruitment during inflammation through synergistic effects on endothelial activation. J Immunol. 2012;188:6287-6299.
Not in our library10.4049/jimmunol.1200385 (opens in a new tab)
- 25.
Czarnowicki T, et al. Severe atopic dermatitis is characterized by selective expansion of circulating TH2/TC2 and TH22/TC22, but not TH17/TC17, cells within the skin-homing T-cell population. J Allergy Clin Immunol. 2015;136:104-115 e107.
Not in our library10.1016/j.jaci.2015.01.020 (opens in a new tab)
- 26.
Koga C, Kabashima K, Shiraishi N, Kobayashi M, Tokura Y. Possible pathogenic role of Th17 cells for atopic dermatitis. J Invest Dermatol. 2008;128:2625-2630.
Not in our library10.1038/jid.2008.111 (opens in a new tab)
- 27.
Berker M, et al. Allergies - A T cells perspective in the era beyond the TH1/TH2 paradigm. Clin Immunol. 2016;174:73-83.
Not in our library10.1016/j.clim.2016.11.001 (opens in a new tab)
- 28.
Liu CL, Zhang JY, Shi GP. Interaction between allergic asthma and atherosclerosis. Transl Res. 2016;174:5-22.
Not in our library10.1016/j.trsl.2015.09.009 (opens in a new tab)
- 29.
Fatkhullina AR, Peshkova IO, Koltsova EK. The Role of Cytokines in the Development of Atherosclerosis. Biochemistry (Mosc). 2016;81:1358-1370.
Not in our library10.1134/s0006297916110134 (opens in a new tab)
- 30.
Czarnowicki T, et al. Skin-homing and systemic T-cell subsets show higher activation in atopic dermatitis versus psoriasis. J Allergy Clin Immunol. 2015;136:208-211.
Not in our library10.1016/j.jaci.2015.03.032 (opens in a new tab)
- 31.
Thijs J, et al. Biomarkers for atopic dermatitis: a systematic review and meta-analysis. Curr Opin Allergy Clin Immunol. 2015;15:453-460.
Not in our library10.1097/aci.0000000000000198 (opens in a new tab)
- 32.
Wu KG, Li TH, Chen CJ, Cheng HI, Wang TY. Correlations of serum Interleukin-16, total IgE, eosinophil cationic protein and total eosinophil counts with disease activity in children with atopic dermatitis. Int J Immunopathol Pharmacol. 2011;24:15-23.
Not in our library10.1177/039463201102400103 (opens in a new tab)
- 33.
Ungar B, et al. An Integrated Model of Atopic Dermatitis Biomarkers Highlights the Systemic Nature of the Disease. J Invest Dermatol. 2017;137:603-613.
Not in our library10.1016/j.jid.2016.09.037 (opens in a new tab)
- 34.
Hayashida S, et al. Significant correlation of serum IL-22 levels with CCL17 levels in atopic dermatitis. J Dermatol Sci. 2011;61:78-79.
Not in our library10.1016/j.jdermsci.2010.08.013 (opens in a new tab)
- 35.
Jahnz-Rozyk K, Targowski T, Paluchowska E, Owczarek W, Kucharczyk A. Serum thymus and activation-regulated chemokine, macrophage-derived chemokine and eotaxin as markers of severity of atopic dermatitis. Allergy. 2005;60:685-688.
Not in our library10.1111/j.1398-9995.2005.00774.x (opens in a new tab)
- 36.
Raap U, et al. IL-31 significantly correlates with disease activity and Th2 cytokine levels in children with atopic dermatitis. Pediatr Allergy Immunol. 2012;23:285-288.
Not in our library10.1111/j.1399-3038.2011.01241.x (opens in a new tab)
- 37.
Otsuka A, et al. Effects of cyclosporine on pruritus and serum IL-31 levels in patients with atopic dermatitis. Eur J Dermatol. 2011;21:816-817.
Not in our library10.1684/ejd.2011.1470 (opens in a new tab)
- 38.
Haeck IM, et al. Enteric-coated mycophenolate sodium versus cyclosporin A as long-term treatment in adult patients with severe atopic dermatitis: a randomized controlled trial. J Am Acad Dermatol. 2011;64:1074-1084.
Not in our library10.1016/j.jaad.2010.04.027 (opens in a new tab)
- 39.
Brunner PM, et al. Increasing Comorbidities Suggest that Atopic Dermatitis Is a Systemic Disorder. J Invest Dermatol. 2017;137:18-25.
Not in our library10.1016/j.jid.2016.08.022 (opens in a new tab)
- 40.
Lind L, et al. Use of a proximity extension assay proteomics chip to discover new biomarkers for human atherosclerosis. Atherosclerosis. 2015;242:205-210.
Not in our library10.1016/j.atherosclerosis.2015.07.023 (opens in a new tab)
- 41.
- 42.
Lundberg M, Eriksson A, Tran B, Assarsson E, Fredriksson S. Homogeneous antibody-based proximity extension assays provide sensitive and specific detection of low-abundant proteins in human blood. Nucleic Acids Res. 2011;39:e102.
Not in our library10.1093/nar/gkr424 (opens in a new tab)
- 43.
Guttman-Yassky E, et al. Low expression of the IL-23/Th17 pathway in atopic dermatitis compared to psoriasis. J Immunol. 2008;181:7420-7427.
Not in our library10.4049/jimmunol.181.10.7420 (opens in a new tab)
- 44.
Wolfram JA, et al. Keratinocyte but not endothelial cell-specific overexpression of Tie2 leads to the development of psoriasis. Am J Pathol. 2009;174:1443-1458.
Not in our library10.2353/ajpath.2009.080858 (opens in a new tab)
- 45.
Kuroda K, Sapadin A, Shoji T, Fleischmajer R, Lebwohl M. Altered expression of angiopoietins and Tie2 endothelium receptor in psoriasis. J Invest Dermatol. 2001;116:713-720.
Not in our library10.1046/j.1523-1747.2001.01316.x (opens in a new tab)
- 46.
Klempel MC, Varady KA. Reliability of leptin, but not adiponectin, as a biomarker for diet-induced weight loss in humans. Nutr Rev. 2011;69:145-154.
Not in our library10.1111/j.1753-4887.2011.00373.x (opens in a new tab)
- 47.
- 48.
Ewald DA, et al. Major differences between human atopic dermatitis and murine models, as determined by using global transcriptomic profiling. J Allergy Clin Immunol. 2017;139:562-571.
Not in our library10.1016/j.jaci.2016.08.029 (opens in a new tab)
- 49.
Rivals I, Personnaz L, Taing L, Potier MC. Enrichment or depletion of a GO category within a class of genes: which test? Bioinformatics. 2007;23:401-407.
Not in our library10.1093/bioinformatics/btl633 (opens in a new tab)
- 50.
Zhang J, et al. Gene ontology and KEGG enrichment analyses of genes related to age-related macular degeneration. Biomed Res Int. 2014;2014:450386.
Not in our library10.1155/2014/450386 (opens in a new tab)
- 51.
Schaefer CF, et al. PID: the Pathway Interaction Database. Nucleic Acids Res. 2009;37:D674-679.
Not in our library10.1093/nar/gkn653 (opens in a new tab)
- 52.
Haw R, Hermjakob H, D’Eustachio P, Stein L. Reactome pathway analysis to enrich biological discovery in proteomics data sets. Proteomics. 2011;11:3598-3613.
Not in our library10.1002/pmic.201100066 (opens in a new tab)
- 53.
Yim KM, Armstrong AW. Updates on cardiovascular comorbidities associated with psoriatic diseases: epidemiology and mechanisms. Rheumatol Int. 2017;37:97-105.
Not in our library10.1007/s00296-016-3487-2 (opens in a new tab)
- 54.
Coumbe AG, Pritzker MR, Duprez DA. Cardiovascular risk and psoriasis: beyond the traditional risk factors. Am J Med. 2014;127:12-18.
Not in our library10.1016/j.amjmed.2013.08.013 (opens in a new tab)
- 55.
Shlyankevich J, et al. Accumulating evidence for the association and shared pathogenic mechanisms between psoriasis and cardiovascular-related comorbidities. Am J Med. 2014;127:1148-1153.
Not in our library10.1016/j.amjmed.2014.08.008 (opens in a new tab)
- 56.
Strom, M. & Silverberg, J. I. Associations of Physical Activity and Sedentary Behavior with Atopic Disease in US Children. J Pediatrics174, 247–253 (2016).
Not in our library10.1016/j.jpeds.2016.03.063 (opens in a new tab)
- 57.
Marshall VD, Moustafa F, Hawkins SD, Balkrishnan R, Feldman SR. Cardiovascular Disease Outcomes Associated with Three Major Inflammatory Dermatologic Diseases: A Propensity-Matched Case Control Study. Dermatol Ther (Heidelb). 2016;6:649-658.
Not in our library10.1007/s13555-016-0144-3 (opens in a new tab)
- 58.
Esaki, H. et al. Early onset pediatric atopic dermatitis is Th2, but also Th17 polarized in skin. J Allergy Clin Immunol, 138, 1639–1651 (2016).
Not in our library10.1016/j.jaci.2016.07.013 (opens in a new tab)
- 59.
Guttman-Yassky E, Nograles KE, Krueger JG. Contrasting pathogenesis of atopic dermatitis and psoriasis–part II: immune cell subsets and therapeutic concepts. J Allergy Clin Immunol. 2011;127:1420-1432.
Not in our library10.1016/j.jaci.2011.01.054 (opens in a new tab)
- 60.
Chen WY, Cheng BC, Jiang MJ, Hsieh MY, Chang MS. IL-20 is expressed in atherosclerosis plaques and promotes atherosclerosis in apolipoprotein E-deficient mice. Arterioscler Thromb Vasc Biol. 2006;26:2090-2095.
Not in our library10.1161/01.atv.0000232502.88144.6f (opens in a new tab)
- 61.
Gronberg C, et al. Human Carotid Plaques With High Levels of Interleukin-16 Are Associated With Reduced Risk for Cardiovascular Events. Stroke. 2015;46:2748-2754.
Not in our library10.1161/strokeaha.115.009910 (opens in a new tab)
- 62.
Gronberg C, et al. Endarterectomy patients with elevated levels of circulating IL-16 have fewer cardiovascular events during follow-up. Cytokine. 2016;85:137-139.
Not in our library10.1016/j.cyto.2016.06.009 (opens in a new tab)
- 63.
Gittler JK, et al. Progressive activation of T(H)2/T(H)22 cytokines and selective epidermal proteins characterizes acute and chronic atopic dermatitis. J Allergy Clin Immunol. 2012;130:1344-1354.
Not in our library10.1016/j.jaci.2012.07.012 (opens in a new tab)
- 64.
Czarnowicki T, et al. Early pediatric atopic dermatitis shows only a cutaneous lymphocyte antigen (CLA)( + ) TH2/TH1 cell imbalance, whereas adults acquire CLA( + ) TH22/TC22 cell subsets. J Allergy Clin Immunol. 2015;136:941-951 e943.
Not in our library10.1016/j.jaci.2015.05.049 (opens in a new tab)
- 65.
Kim J, Krueger JG. The immunopathogenesis of psoriasis. Dermatol Clin. 2015;33:13-23.
Not in our library10.1016/j.det.2014.09.002 (opens in a new tab)
- 66.
Sprague AH, Khalil RA. Inflammatory cytokines in vascular dysfunction and vascular disease. Biochem Pharmacol. 2009;78:539-552.
Not in our library10.1016/j.bcp.2009.04.029 (opens in a new tab)
- 67.
Dowlatshahi EA, van der Voort EA, Arends LR, Nijsten T. Markers of systemic inflammation in psoriasis: a systematic review and meta-analysis. Br J Dermatol. 2013;169:266-282.
Not in our library10.1111/bjd.12355 (opens in a new tab)
- 68.
Ryan C, Kirby B. Psoriasis is a systemic disease with multiple cardiovascular and metabolic comorbidities. Dermatol Clin. 2015;33:41-55.
Not in our library10.1016/j.det.2014.09.004 (opens in a new tab)
- 69.
Davidovici BB, et al. Psoriasis and systemic inflammatory diseases: potential mechanistic links between skin disease and co-morbid conditions. J Invest Dermatol. 2010;130:1785-1796.
Not in our library10.1038/jid.2010.103 (opens in a new tab)
- 70.
Mansouri Y, Guttman-Yassky E. Immune Pathways in Atopic Dermatitis, and Definition of Biomarkers through Broad and Targeted Therapeutics. J Clin Med. 2015;4:858-873.
Not in our library10.3390/jcm4050858 (opens in a new tab)
- 71.
Johnston A, et al. Keratinocyte overexpression of IL-17C promotes psoriasiform skin inflammation. J Immunol. 2013;190:2252-2262.
Not in our library10.4049/jimmunol.1201505 (opens in a new tab)
- 72.
Butcher MJ, Waseem TC, Galkina EV. Smooth Muscle Cell-Derived Interleukin-17C Plays an Atherogenic Role via the Recruitment of Proinflammatory Interleukin-17A + T Cells to the Aorta. Arterioscler Thromb Vasc Biol. 2016;36:1496-1506.
Not in our library10.1161/atvbaha.116.307892 (opens in a new tab)
- 73.
Golden JB, et al. Chronic Psoriatic Skin Inflammation Leads to Increased Monocyte Adhesion and Aggregation. J Immunol. 2015;195:2006-2018.
Not in our library10.4049/jimmunol.1402307 (opens in a new tab)
- 74.
Karbach S, et al. Interleukin 17 drives vascular inflammation, endothelial dysfunction, and arterial hypertension in psoriasis-like skin disease. Arterioscler Thromb Vasc Biol. 2014;34:2658-2668.
Not in our library10.1161/atvbaha.114.304108 (opens in a new tab)
- 75.
Cohavy O, Zhou J, Ware CF, Targan SR. LIGHT is constitutively expressed on T and NK cells in the human gut and can be induced by CD2-mediated signaling. J Immunol. 2005;174:646-653.
Not in our library10.4049/jimmunol.174.2.646 (opens in a new tab)
- 76.
Kim WJ, et al. LIGHT is involved in the pathogenesis of rheumatoid arthritis by inducing the expression of pro-inflammatory cytokines and MMP-9 in macrophages. Immunology. 2005;114:272-279.
Not in our library10.1111/j.1365-2567.2004.02004.x (opens in a new tab)
- 77.
Lee WH, et al. Tumor necrosis factor receptor superfamily 14 is involved in atherogenesis by inducing proinflammatory cytokines and matrix metalloproteinases. Arterioscler Thromb Vasc Biol. 2001;21:2004-2010.
Not in our library10.1161/hq1201.098945 (opens in a new tab)
- 78.
Muller A, et al. Gene expression levels of matrix metalloproteinases in human atherosclerotic plaques and evaluation of radiolabeled inhibitors as imaging agents for plaque vulnerability. Nucl Med Biol. 2014;41:562-569.
Not in our library10.1016/j.nucmedbio.2014.04.085 (opens in a new tab)
- 79.
Simpson EL, et al. Two Phase 3 Trials of Dupilumab versus Placebo in Atopic Dermatitis. N Engl J Med. 2016;15:2335-2348.
Not in our library10.1056/nejmoa1610020 (opens in a new tab)
- 80.
Bagnasco D, Ferrando M, Varricchi G, Passalacqua G, Canonica GW. A Critical Evaluation of Anti-IL-13 and Anti-IL-4 Strategies in Severe Asthma. Int Arch Allergy Immunol. 2016;170:122-131.
Not in our library10.1159/000447692 (opens in a new tab)
- 81.
Braunersreuther V, Mach F, Steffens S. The specific role of chemokines in atherosclerosis. Thromb Haemost. 2007;97:714-721.
Not in our library10.1160/th07-01-0036 (opens in a new tab)
- 82.
Imaizumi T, Yoshida H, Satoh K. Regulation of CX3CL1/fractalkine expression in endothelial cells. J Atheroscler Thromb. 2004;11:15-21.
Not in our library10.5551/jat.11.15 (opens in a new tab)
- 83.
Chang TT, Chen JW. Emerging role of chemokine CC motif ligand 4 related mechanisms in diabetes mellitus and cardiovascular disease: friends or foes? Cardiovasc Diabetol. 2016;15:117.
Not in our library10.1186/s12933-016-0439-9 (opens in a new tab)
- 84.
Rousselle A, et al. CXCL5 limits macrophage foam cell formation in atherosclerosis. J Clin Invest. 2013;123:1343-1347.
Not in our library10.1172/jci66580 (opens in a new tab)
- 85.
Scanlon KM, Hawksworth RJ, Lane SJ, Mahon BP. IL-17A induces CCL28, supporting the chemotaxis of IgE-secreting B cells. Int Arch Allergy Immunol. 2011;156:51-61.
Not in our library10.1159/000322178 (opens in a new tab)
- 86.
Weber C, et al. CCL17-expressing dendritic cells drive atherosclerosis by restraining regulatory T cell homeostasis in mice. J Clin Invest. 2011;121:2898-2910.
Not in our library10.1172/jci44925 (opens in a new tab)
- 87.
Tavakolian Ferdousie V, et al. Serum CXCL10 and CXCL12 chemokine levels are associated with the severity of coronary artery disease and coronary artery occlusion. Int J Cardiol. 2017;233:23-28.
Not in our library10.1016/j.ijcard.2017.02.011 (opens in a new tab)
- 88.
Mazidi, M. et al. VEGF, the underlying factor for metabolic syndrome; fact or fiction? Diabetes Metab Syndr Epub ahead of print. (2016).
Not in our library10.1016/j.dsx.2016.12.004 (opens in a new tab)
- 89.
Konya H, et al. Hepatocyte growth factor, a biomarker of macroangiopathy in diabetes mellitus. World J Diabetes. 2014;5:678-688.
Not in our library10.4239/wjd.v5.i5.678 (opens in a new tab)
- 90.
Bell EJ, et al. Hepatocyte Growth Factor Is Positively Associated With Risk of Stroke: The MESA (Multi-Ethnic Study of Atherosclerosis). Stroke. 2016;47:2689-2694.
Not in our library10.1161/strokeaha.116.014172 (opens in a new tab)
- 91.
Gotsman I, Sharpe AH, Lichtman AH. T-cell costimulation and coinhibition in atherosclerosis. Circ Res. 2008;103:1220-1231.
Not in our library10.1161/circresaha.108.182428 (opens in a new tab)
- 92.
Olofsson PS, et al. CD137 is expressed in human atherosclerosis and promotes development of plaque inflammation in hypercholesterolemic mice. Circulation. 2008;117:1292-1301.
Not in our library10.1161/circulationaha.107.699173 (opens in a new tab)
- 93.
Lee JH, et al. Association Between Metabolic Syndrome and Atopic Dermatitis in Korean Adults. Acta Derm Venereol. 2017;96:77-80.
Not in our library10.2340/00015555-2441 (opens in a new tab)
- 94.
Soderlund S, et al. Plasma proteomics in CML patients before and after initiation of tyrosine kinase inhibitor therapy reveals induced Th1 immunity and loss of angiogenic stimuli. Leuk Res. 2016;50:95-103.
Not in our library10.1016/j.leukres.2016.09.019 (opens in a new tab)
- 95.
Khattri S, et al. Cyclosporine in patients with atopic dermatitis modulates activated inflammatory pathways and reverses epidermal pathology. J Allergy Clin Immunol. 2014;133:1626-1634.
Not in our library10.1016/j.jaci.2014.03.003 (opens in a new tab)
- 96.
Suarez-Farinas M, et al. RNA sequencing atopic dermatitis transcriptome profiling provides insights into novel disease mechanisms with potential therapeutic implications. J Allergy Clin Immunol. 2015;135:1218-1227.
Not in our library10.1016/j.jaci.2015.03.003 (opens in a new tab)
- 97.
Smyth, G. K. Linear models and empirical Bayes methods for assessing differential expression in microarray experiments. Stat Appl Genet Mol Biol3, Article 3 (2004).
Not in our library10.2202/1544-6115.1027 (opens in a new tab)
- 98.
- 99.
Kanehisa M, Goto S, Furumichi M, Tanabe M, Hirakawa M. KEGG for representation and analysis of molecular networks involving diseases and drugs. Nucleic Acids Res. 2010;38:D355-360.
Not in our library10.1093/nar/gkp896 (opens in a new tab)
- 100.
Nishimura D. BioCarta. Biotech Software & Internet Report. 2001;2:117-120.
Not in our library10.1089/152791601750294344 (opens in a new tab)
- 101.
- 102.
Subramanian A, et al. Gene set enrichment analysis: a knowledge-based approach for interpreting genome-wide expression profiles. Proc Natl Acad Sci USA. 2005;102:15545-15550.
Not in our library10.1073/pnas.0506580102 (opens in a new tab)
Cited by papers we hold4
Reads
Read by people on this page
None yet.
Checked or read by AI through naulon
None yet.
A person counts once a day per paper. We keep no cookie and no address: a reader is a hash that changes every day. Any month under five reads shows no number.
Are you an author?
Is this your paper?
Claim it to add your note and be paid when agents cite it. Free.